



Advances in the non-invasive assessment of metabolic dysfunction-associated steatotic liver disease
 0
Abstract
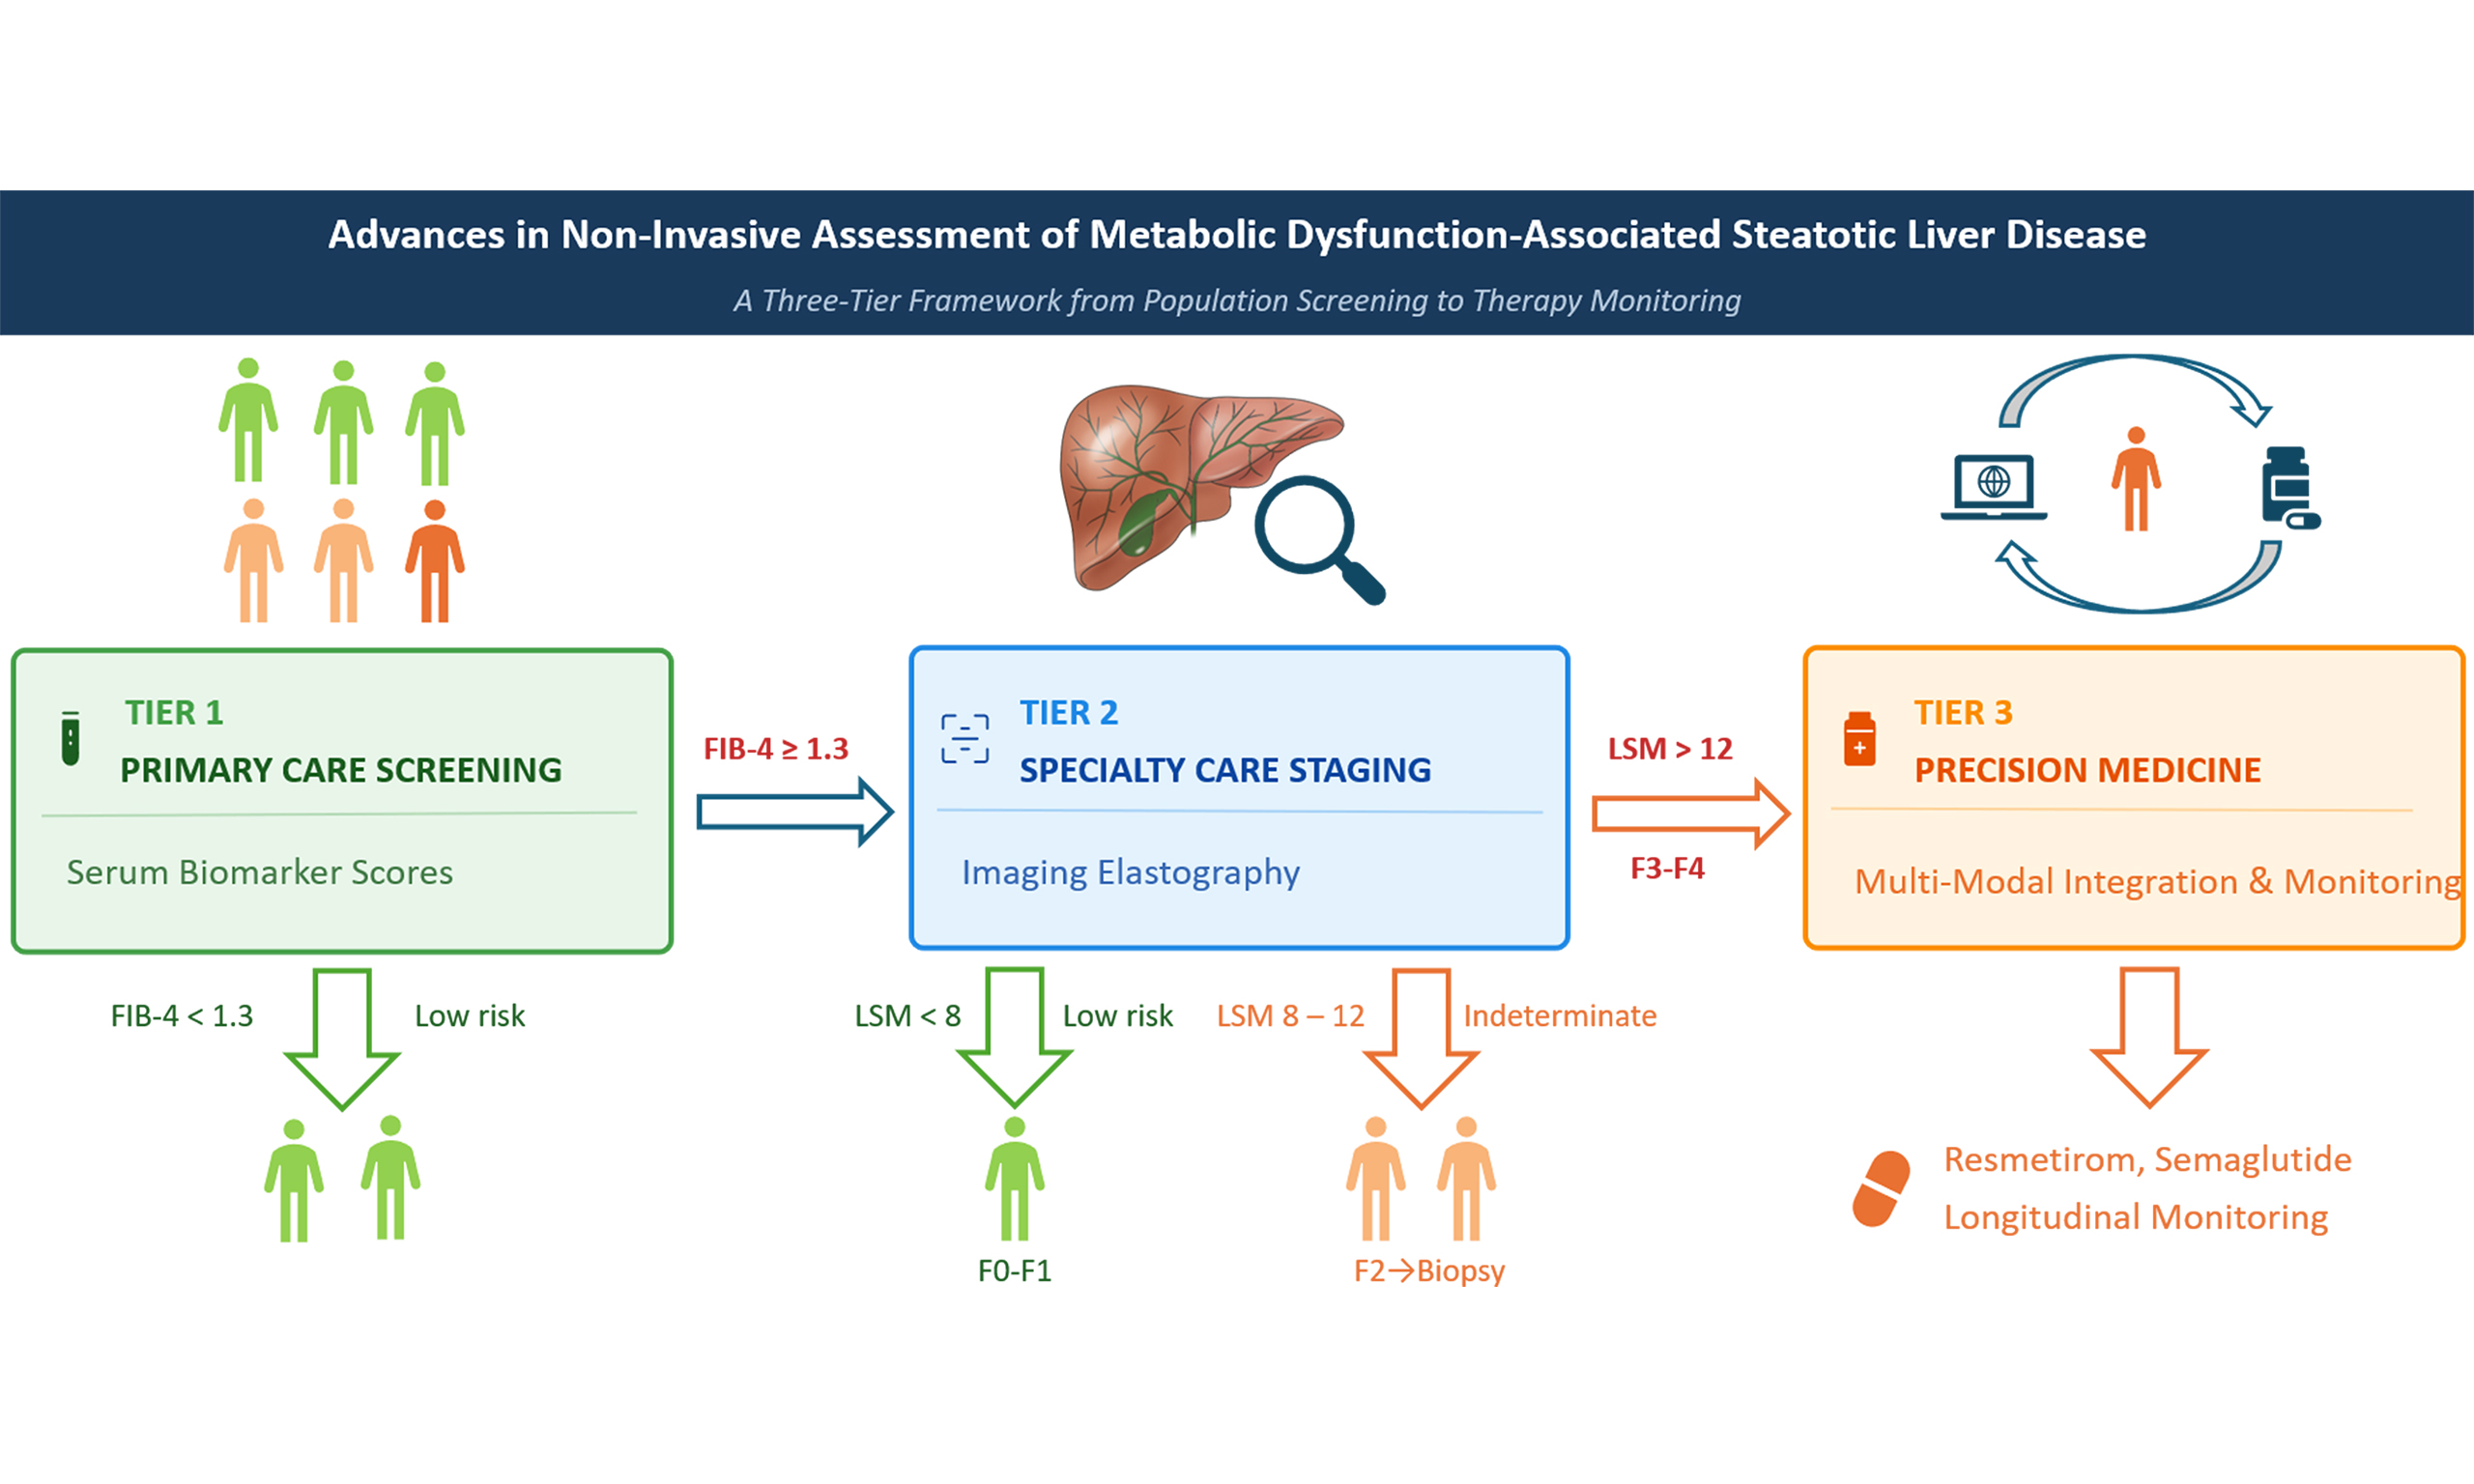
Metabolic dysfunction-associated steatotic liver disease (MASLD) affects approximately 30% of adults worldwide. Liver biopsy remains the reference standard but is unsuitable for population-wide screening due to its invasiveness and cost. This review summarizes recent advances in non-invasive tests (NITs) for MASLD and proposes a conceptual three-tier framework to guide clinical practice. First-tier serum biomarker scores enable low-cost initial risk stratification in primary care. Second-tier imaging elastography techniques provide objective quantification of liver stiffness and steatosis for fibrosis staging. Third-tier emerging artificial intelligence (AI) and multi-modal integration models remain investigational but hold promise for precise subtyping. Despite substantial progress, challenges persist in accessibility, standardization, and cost-effectiveness. With the recent Food and Drug Administration (FDA) approvals of resmetirom and semaglutide for metabolic dysfunction-associated steatohepatitis (MASH) with moderate-to-advanced fibrosis (F2-F3), and the acceptance of vibration-controlled transient elastography (VCTE) as a surrogate endpoint, NITs have become essential for patient selection, treatment monitoring, and longitudinal disease management. Future directions include multi-omics integration and AI-empowered clinical decision support, enabling a shift toward personalized, metabolic-driven care.
Keywords
INTRODUCTION
Metabolic dysfunction-associated steatotic liver disease (MASLD), previously termed non-alcoholic fatty liver disease (NAFLD), is the most prevalent chronic liver disease worldwide, affecting up to 30% of adults[1]. In Asian populations, its prevalence is rising rapidly, mirroring the increasing rates of obesity and type 2 diabetes (T2D)[2]. Rather than a simple hepatic manifestation of metabolic syndrome, MASLD is bidirectionally associated with metabolic dysfunction: obesity, insulin resistance, and T2D promote MASLD progression, while MASLD itself exacerbates systemic insulin resistance and cardiometabolic risk[3]. Approximately 20% of patients with MASLD progress to metabolic dysfunction-associated steatohepatitis (MASH) and liver fibrosis, which is the strongest predictor of liver-related complications - including cirrhosis, liver failure, and hepatocellular carcinoma - as well as all-cause mortality. Furthermore, patients with MASLD have more than a 40% higher risk of cardiovascular and cerebrovascular events than the general population, constituting a substantial global public health burden[4-6].
The introduction of the MASLD nomenclature marks a fundamental paradigm shift in disease diagnosis, supplementing the exclusion-based logic of the NAFLD era with positive diagnostic criteria based on hepatic steatosis and cardiometabolic risk factors. The diagnosis of MASLD requires the fulfilment of the following two criteria: (1) confirmation of hepatic fat content ≥ 5% by imaging or histology; and (2) the presence of at least one of the following cardiometabolic risk factors: (1) overweight or obesity [body mass index (BMI) ≥ 25 kg/m2 for non-Asian populations, or ≥ 23 kg/m2 for Asian populations]; (2) T2D; (3) dysglycemia [fasting plasma glucose ≥ 5.6 mmol/L or glycated hemoglobin (HbA1c) ≥ 5.7%]; (4) elevated blood pressure (systolic blood pressure ≥ 130 mmHg or diastolic blood pressure ≥ 85 mmHg, or receiving antihypertensive treatment); and (5) dyslipidemia [triglycerides ≥ 1.7 mmol/L, or high-density lipoprotein (HDL) cholesterol < 1.0 mmol/L in men or < 1.3 mmol/L in women, or receiving lipid-lowering treatment][2,7]. This transition streamlines the diagnostic process and underscores the central role of metabolic dysfunction in disease pathophysiology, establishing a clearer rationale for the use of non-invasive tests (NITs).
Liver biopsy has long been regarded as the reference standard for assessing liver histology (steatosis, inflammation, fibrosis) in chronic liver disease, including under the earlier NAFLD/non-alcoholic steatohepatitis (NASH) nomenclature. Since the introduction of the MASLD nomenclature in 2023, it remains the histological reference standard for MASLD. However, its invasive complications, sampling error (representing only 1/50,000 of liver volume), high cost, and poor reproducibility render it unsuitable for large-scale population screening, longitudinal monitoring, and treatment response assessment[8-10]. Given the large MASLD patient population, primary care urgently needs convenient, low-cost tools to identify high-risk individuals, whereas specialized care requires precise stratification to optimize intervention strategies. These clinical needs have spurred rapid innovation in NITs.
NITs now constitute a multi-tiered system. Serum biomarker scoring systems [e.g., fibrosis-4 index (FIB-4), LiverRisk] serve as the frontline tools for primary screening because of their low cost[11,12]; imaging elastography techniques (e.g., vibration-controlled transient elastography (VCTE), magnetic resonance elastography (MRE)) are the core modalities for fibrosis staging given their quantitative capabilities[13,14]; and artificial intelligence (AI) combined with multi-modal integration models enable more accurate risk prediction and early detection through analysis of high-dimensional data[15,16]. Major guidelines have incorporated NITs into clinical pathways[2]. In August 2025, the Food and Drug Administration (FDA) accepted a Letter of Intent for the qualification of liver stiffness measurement (LSM) by VCTE as a reasonably likely surrogate endpoint for clinical trials in adults with non-cirrhotic MASH with moderate-to-advanced fibrosis[17,18], cementing its transition from an adjunct tool to a central modality for fibrosis risk stratification and treatment monitoring.
Until recently, no pharmacological therapies were approved for MASH. In March 2024, the FDA granted accelerated approval to resmetirom, a thyroid hormone receptor-β agonist, for the treatment of non-cirrhotic MASH with F2-F3 fibrosis[19]. In August 2025, semaglutide 2.4 mg, a glucagon-like peptide-1 (GLP-1) receptor agonist, received accelerated approval for the same indication based on the phase 3 ESSENCE trial, which demonstrated resolution of steatohepatitis without worsening of fibrosis in 62.9% of participants (vs. 34.3% placebo) and ≥ 1-stage fibrosis improvement in 36.8% (vs. 22.4% placebo)[20]. These approvals establish two distinct pharmacotherapy classes for MASH and reinforce the central role of NITs in patient selection and treatment monitoring. The approval of two distinct pharmacotherapy classes for non-cirrhotic MASH with F2-F3 fibrosis underscores the need for reliable non-invasive monitoring tools. In the pharmacotherapy era, NITs are evolving from cross-sectional diagnostic tools into longitudinal instruments for assessing treatment response and detecting futility, which is essential for guiding clinical decisions.
This review summarizes recent advances in NITs for MASLD, covering serum biomarkers, imaging technologies, and AI applications, including their classification, clinical performance, and practical use cases. It also analyzes clinical pathways and stratified management strategies based on current guideline recommendations, and discusses future directions such as multi-omics integration and dynamic monitoring, with the goal of providing clinicians with a comprehensive reference for precise, individualized MASLD management.
We conducted a narrative review of the literature. PubMed and Web of Science were searched from inception to August 2026. The search strategy combined terms related to MASLD/NAFLD/MASH/NASH and NITs, including: (“MASLD” OR “NAFLD” OR “MASH” OR “NASH”) AND (“non-invasive test” OR “serum biomarker” OR “FIB-4” OR “NFS” OR “ELF” OR “LiverRisk” OR “SAFE” OR “Agile” OR “MAST” OR “MEFIB” OR “elastography” OR “VCTE” OR “MRE” OR “SWE” OR “quantitative ultrasound” OR “artificial intelligence”). Reference lists of relevant guidelines and reviews were also hand-searched. Inclusion criteria were original studies, systematic reviews/meta-analyses, clinical practice guidelines, and consensus statements published in English involving adult patients with MASLD/NAFLD. Exclusion criteria were conference abstracts, editorials, case reports, letters, and studies not reporting relevant diagnostic performance or clinical outcomes. Conference abstracts were generally excluded, except for highly relevant emerging data (e.g., novel AI applications) where no full-text publication was yet available at the time of the search. Titles and abstracts were independently screened by two reviewers, followed by full-text review of potentially eligible studies.
EVOLUTION OF DISEASE DEFINITION AND DIAGNOSTIC CRITERIA
Nomenclature evolution: from NAFLD, MAFLD to MASLD
The definition and diagnostic criteria for MASLD have undergone a fundamental paradigm shift in recent years, transitioning from an exclusion-based diagnosis (NAFLD) to a positive, criteria-based diagnosis (MASLD) based on hepatic steatosis and metabolic risk factors[2,21]. This shift not only simplifies the clinical diagnostic process but also lays a clearer foundation for the application of NITs. The term NAFLD has been widely used since 1980. Its diagnosis relied on an exclusion-based approach: ruling out excessive alcohol consumption (≤ 30 g/day for men, ≤ 20 g/day for women) and other specific liver disease etiologies, while confirming hepatic steatosis[22]. This diagnostic framework did not explicitly acknowledge the central roles of obesity, insulin resistance, and metabolic syndrome in disease pathogenesis, and the term itself carried stigmatizing connotations[21]. To address this limitation, an international panel of experts proposed in 2020 the term “metabolic associated fatty liver disease (MAFLD)”, advocating for a definition based on positive metabolic criteria - a pivotal shift from “what to exclude” to “what to include”[22]. Following extensive consultation, the 2023 multi-society Delphi consensus - involving the American Association for the Study of Liver Diseases (AASLD), the European Association for the Study of the Liver (EASL), and other major societies - officially adopted the term “MASLD” to promote global uniformity in clinical practice and research[2]. This change renders the diagnostic process more intuitive and practical, encourages clinicians to actively screen for metabolic risk factors, acknowledges that multiple liver diseases frequently coexist in clinical practice, and formally establishes metabolic dysfunction as the central disease paradigm[21,22]. Beyond pathophysiological considerations, concerns over patient stigmatization associated with the term “fatty” also contributed to the nomenclature change[21].
However, the evidence for stigma as a primary driver of nomenclature change is more nuanced than commonly assumed. A global survey across 21 countries (1,976 patients and 825 providers) found a marked discordance: only 8% of patients reported having experienced stigmatization due to NAFLD, whereas 38% of providers believed the term “fatty” was stigmatizing. Moreover, 26% of patients reported stigma related to overweight/obesity - more than three times the rate attributable to the disease name itself. Stigma perception varied substantially by region, ranging from 22% in the USA to 3% in the Middle East and North Africa for disease-name-related stigma[23]. This regional variation may partly reflect cultural factors: in some settings, plumpness is regarded as a positive sign of prosperity, fertility, and health rather than a health risk. Notably, physicians’ own attitudes may contribute to internalized self-stigma: 46% of providers reported discomfort in caring for patients with NAFLD, viewing them as lacking willpower or self-control, while 33% of patients believed they were at least partly to blame for their liver disease[24]. These findings suggest that the rationale for renaming is not a universally experienced patient-level stigma, but a more complex interplay of provider perception, cultural context, and internalized blame.
Detailed 2023 multi-society consensus diagnostic criteria
The diagnostic criteria for MASLD follow a positive-definition approach, comprising one mandatory criterion and at least one concomitant criterion[2]:
Mandatory criterion (Hepatic steatosis)
Confirmation of hepatic fat content ≥ 5% by imaging [e.g., ultrasound, controlled attenuation parameter (CAP), magnetic resonance imaging-proton density fat fraction (MRI-PDFF)] or histology. Notably, blood biomarkers are not accepted as a standalone method for confirming steatosis, which represents a subtle but important distinction from the MAFLD criteria.
Concomitant criteria (Cardiometabolic risk factors - at least one of the following must be present)
(1) Overweight or obesity: BMI ≥ 25 kg/m2 for non-Asian populations or ≥ 23 kg/m2 for Asian populations; and/or waist circumference exceeding ethnicity- and sex-specific thresholds (e.g. ≥ 94 cm in men and ≥
(2) Type 2 diabetes: HbA1c ≥ 6.5% (≥ 48 mmol/mol), or fasting plasma glucose ≥ 7.0 mmol/L (≥ 126 mg/dL), or receiving glucose-lowering therapy.
(3) Dysglycemia (prediabetes): HbA1c 5.7%-6.4% (39-47 mmol/mol), or fasting plasma glucose 5.6-
(4) Elevated blood pressure: Systolic blood pressure ≥ 130 mmHg and/or diastolic blood pressure ≥
(5) Dyslipidemia: Plasma triglycerides ≥ 1.7 mmol/L (≥ 150 mg/dL), or HDL < 1.0 mmol/L (< 39 mg/dL) in men or < 1.3 mmol/L (< 50 mg/dL) in women, or receiving lipid-lowering therapy.
Alcohol consumption and disease sub-classification
Alcohol intake must be carefully quantified in all patients with steatotic liver disease, as it determines sub-classification: MASLD (≤ 20 g/day for women, ≤ 30 g/day for men), metabolic and alcohol-associated liver disease (MetALD) (> 20 to ≤ 50 g/day for women, > 30 to ≤ 60 g/day for men), and alcoholic liver disease (ALD) (> 50 g/day for women, > 60 g/day for men)[2]. This distinction acknowledges that metabolic dysfunction and alcohol-related liver injury frequently coexist.
Diagnostic work-up and exclusion of other aetiologies
The diagnosis of MASLD is established by confirming hepatic steatosis and at least one cardiometabolic risk factor, together with the exclusion of other specific causes of steatotic liver disease[21]. Exclusion of other aetiologies is therefore an integral component of the diagnostic process, rather than a secondary consideration. While the new nomenclature has shifted the diagnostic emphasis toward positive metabolic criteria, the exclusion of other causes remains essential to confirm the diagnosis[2]. In contrast, the previous MAFLD definition allowed a diagnosis based on metabolic criteria alone without requiring exclusion of other aetiologies, which was a key point of divergence[22].
Comparison of old and new diagnostic paradigms and clinical significance
The table below clearly compares the core differences between the NAFLD and MASLD diagnostic paradigms [Table 1][2,21,22,25]:
Core differences in diagnostic paradigms between NAFLD and MASLD
| Comparison dimension | NAFLD | MASLD | MAFLD |
| Year proposed/authors | 1980; Ludwig et al.[25] | 2020; Eslam et al.[22] | 2023; Rinella et al. (multisociety Delphi consensus)[21] |
| Diagnostic logic | Exclusion-based, negative definition: requires exclusion of other liver disease etiologies[22] | Positive, affirmative definition: based on existing metabolic abnormalities and steatosis[2,21] | Positive definition based on hepatic steatosis plus at least one cardiometabolic risk factor, together with exclusion of other specific causes |
| Required evidence | Confirm steatosis + exclude other etiologies (especially alcohol) | Confirmation of hepatic steatosis (≥ 5% by imaging, or histology) + confirmation of at least one cardiometabolic risk factor (see criteria below)[2,21] | Confirm steatosis (≥ 5% by imaging or histology; blood biomarkers not accepted as standalone) + at least one cardiometabolic risk factor |
| Cardiometabolic risk factors | Not required for diagnosis | Core diagnostic component; at least one of the following five criteria must be met: ① Overweight/obesity (non-Asian BMI ≥ 25 kg/m2, Asian BMI ≥ 23 kg/m2); ② T2D; ③ Dysglycemia (fasting glucose ≥ 5.6 mmol/L or HbA1c ≥ 5.7%); ④ Elevated blood pressure (≥ 130/85 mmHg or on antihypertensive therapy); ⑤ Dyslipidemia (triglycerides ≥ 1.7 mmol/L, or HDL-C < 1.0 mmol/L in men/< 1.3 mmol/L in women; or on lipid-lowering therapy)[2,21] | At least one of five criteria: overweight/obesity (non-Asian BMI ≥ 25 kg/m2, Asian ≥ 23 kg/m2), T2D, dysglycemia, elevated blood pressure, dyslipidemia |
| Alcohol consumption | Requires exclusion of “significant” alcohol intake (thresholds vary by guideline) | Quantified and integrated into sub-classification: MASLD (≤ 20 g/day for women, ≤ 30 g/day for men), MetALD (> 20 to ≤ 50 g/day for women, > 30 to ≤ 60 g/day for men), ALD (> 50 g/day for women, > 60 g/day for men)[2,21] | Quantified and integrated into sub-classification: MASLD (≤ 20 g/day women, ≤ 30 g/day men); MetALD (> 20-50 g/day women, > 30-60 g/day men); ALD (> 50 g/day women, >60 g/day men) |
| Relationship with other liver diseases | Mutually exclusive: diagnosing NAFLD requires excluding other liver diseases | Coexistent: can be diagnosed together with other liver diseases such as viral hepatitis | Coexistent: can be diagnosed together with other liver diseases |
| Patient labeling | May imply stigmatization of “non-alcoholic” | More accurately reflects the metabolic nature of the disease | Avoids “fatty” and “non-alcoholic”; more accurately reflects metabolic nature |
The new MASLD diagnostic criteria strengthen the central role of NITs in clinical practice. Because diagnosis no longer requires liver biopsy to exclude other etiologies, the assessment focus shifts to confirming hepatic steatosis ≥ 5% and evaluating both metabolic risk and fibrosis stage. Imaging techniques (e.g., ultrasound, CAP, MRI-PDFF) and serum biomarkers/scores (for assessing metabolic abnormalities and fibrosis risk) are well suited as non-invasive tools for these purposes. Thus, NITs have evolved from a supporting role to central components of MASLD diagnosis, risk stratification, and comprehensive management.
FIRST-LEVEL ASSESSMENT: SERUM BIOMARKER SCORING SYSTEMS
It is important to note that the diagnostic performance of all NITs varies with disease prevalence and pre-test probability; most are better suited for ruling out advanced fibrosis (high negative predictive value, NPV) than for ruling in (low positive predictive value, PPV in low-prevalence settings), supporting the use of sequential testing strategies[2]. This heterogeneity is not merely statistical noise but reflects systematic, clinically meaningful variation across patient subgroups. In a multinational cohort of 18,759 biopsy-confirmed MASLD patients, FIB-4 accuracy declined from an area under the receiver operating characteristic curve (AUROC) of 0.79 in patients < 65 years to 0.70 in those ≥ 65 years, and LSM performance deteriorated progressively with increasing BMI, with the required cutoff for 80% sensitivity rising from 8.8 kPa in lean patients to 11.0 kPa in those with morbid obesity[26]. Real-world data further show that FIB-4 misses approximately 38% of patients with LSM ≥ 8.1 kPa and 35% with LSM ≥ 12.1 kPa in referral pathways[27]. These discordant findings are substantially attributable to spectrum bias: NITs developed and validated in secondary/tertiary care - where advanced fibrosis prevalence is high and the case mix is skewed toward more severe disease - exhibit inflated PPV that are not reproducible when applied to primary care populations with low prevalence. NAFLD fibrosis score (NFS) is particularly vulnerable in this regard because diabetes status is embedded in its formula, leading to systematically elevated scores and reduced PPV in the very population (T2D) where risk stratification is most needed[28]. Recognizing these context-dependent limitations is essential for interpreting any single NIT result and for designing pathways that avoid both over-referral in low-prevalence settings and under-detection in high-risk subgroups. Serum biomarker scoring systems are derived from routine or specific blood tests; these parameters are integrated via formulas or algorithms into scores that indirectly reflect hepatic inflammation, fibrosis, or functional changes. Their pathological basis is that peripheral blood indices can indirectly reflect changes in liver function, portal hypertension, and systemic metabolic status associated with liver fibrosis [Table 2].
Summary of characteristics of major serum scoring systems
| Scoring system | Core variables | Diagnostic performance (Advanced fibrosis) | Advantages | Limitations | Clinical positioning |
| FIB-4 index[29,30] | Age, AST, ALT, platelets | AUROC 0.65-0.80, high NPV | Very low cost, extensively validated, guideline-preferred | Age bias, high grey zone proportion | First-line screening, preferred in primary care |
| NFS[37] | Age, BMI, glucose, platelets, albumin, AST/ALT | AUROC 0.82-0.88 | Incorporates metabolic parameters, easy to calculate | Diabetes-dependent, overestimates risk | First-line screening alongside FIB-4 |
| ELF test[39] | HA, PIIINP, TIMP-1 | AUROC 0.77-0.94 | Directly reflects ECM metabolism, high predictive value | Higher cost, limited accessibility | Second-line confirmation, for indeterminate cases |
| SAFE score[44] | Age, BMI, diabetes, platelets, AST, ALT, globulin | AUROC 0.80-0.83 | Well-validated in Asian populations | Requires further external validation | Primary care, metabolic populations |
| ADAPT[41,42] | Age, diabetes, PRO-C3, platelet count | AUROC 0.86-0.87 (≥ F3) | Superior to APRI and NFS; no liver enzymes; validated in multi-national cohort; no indeterminate zone | Requires PRO-C3 assay (limited availability); higher cost than simple serum indices | Secondary/confirmatory assessment; advanced fibrosis identification |
| LiverRisk score[43] | Age, sex, AST, ALT, GGT, fasting glucose, cholesterol, platelet count | AUROC 0.83 (for LSM ≥ 10 kPa), AUROC 0.90 for 10-year liver-related mortality | Includes GGT, glucose, and cholesterol; fine risk stratification | Insufficiently validated for broader use | Risk stratification, prognosis prediction |
| Agile 3+/4[49] | LSM, platelets, AST, ALT, diabetes, sex, age (Agile 4 excludes age) | AUROC 0.86-0.94 | Best diagnostic performance; integrates imaging | Dependent on VCTE device | Precise stratification in specialty care |
| MAST[51] | MRE-LSM, MRI-PDFF, AST | AUROC 0.93 for Fibro-NASH; cut-offs: < 0.165/> 0.242 | MRI-based; outperforms FAST, FIB-4, NFS; predicts liver-related outcomes; narrow grey zone | Requires MRE/MRI; high cost; limited availability | Specialty care; candidate selection for pharmacotherapy |
| MEFIB[52] | MRE ≥ 3.3 kPa + FIB-4 ≥ 1.6 | AUROC 0.84-0.90 | Simple binary rule-in; high PPV; validated in Asian population; easy to apply | Binary (not continuous); requires MRE; misses 44% of cases | Specialty care; rule-in tool for significant fibrosis; clinical trial enrichment |
| FibroSure[53] | α2-M, Hp, ApoA1, GGT, TBil, γ globulin | AUROC 0.86 (F2-F4)/0.92 (F4) | High accuracy for diagnosing cirrhosis | Affected by inflammation, hemolysis | Combined use, comprehensive assessment |
FIB-4 Index
The FIB-4 index is among the most widely used serum scoring systems for liver fibrosis in clinical practice. Its formula integrates four routine clinical parameters: age, aspartate aminotransferase (AST), alanine aminotransferase (ALT), and platelet count. Because all variables are obtained from routine tests at no additional cost, FIB-4 is a highly cost-effective and readily accessible initial screening tool[2,29,30].
In clinical practice, the FIB-4 index guides decision-making through clearly defined risk stratification thresholds. The exclusion threshold is set at FIB-4 < 1.3, yielding a very high NPV for ruling out advanced fibrosis (F3-F4)[31], rendering it particularly suitable for primary care. The referral threshold of FIB-4 > 2.67 indicates an increased likelihood of advanced fibrosis or cirrhosis in specialty care settings, although PPV vary substantially with disease prevalence and should not be interpreted as fixed test properties[2]. Patients with scores above this threshold warrant referral for further evaluation[2,32]. However, for patients with scores in the grey zone (1.3-2.67), the fibrosis stage remains highly uncertain, and second-line imaging assessment - such as VCTE - is often required for further risk stratification.
Despite its core advantages (low cost, simple calculation, extensive validation, and high NPV), recent studies have identified several limitations. First, the index exhibits age bias, with potentially limited accuracy in young (< 35 years) and elderly patients; particularly in those over 65 years of age, FIB-4 may yield false-positive results. To improve specificity in this age group, the EASL guidelines recommend using a higher lower threshold of 2.0 (instead of 1.3) for ruling out advanced fibrosis, while the upper threshold of 2.67 remains unchanged[33]. Second, because thrombocytopenia and elevated transaminases are not liver-specific, FIB-4 has limited ability to distinguish hepatic inflammation from fibrosis, and its diagnostic accuracy may be compromised in patients with severe obesity or metabolic comorbidities[34]. Third, the performance of FIB-4 is particularly suboptimal in higher-risk populations, especially in patients with T2D, where it has been shown to yield high false-positive rates and limited specificity, prompting some guidelines to question its routine use as a first-line screening tool in this population[34,35]. Given these limitations, FIB-4 is often recommended as an initial screening tool to identify low-risk individuals and avoid unnecessary referrals, whereas patients with indeterminate results require sequential evaluation using further testing[35]. In addition, FIB-4 may reflect systemic congestion rather than liver fibrosis alone, as supported by its prognostic value in heart failure[36].
NFS
The NFS is another widely used serum-based scoring tool[37]. It integrates routine clinical parameters - including age, BMI, fasting glucose or diabetes status, platelet count, albumin, and the AST/ALT ratio - for fibrosis risk assessment. In clinical stratification, NFS and FIB-4 are often recommended as first-line screening tools to identify the risk of advanced fibrosis, thereby optimizing referral pathways and reducing unnecessary liver biopsies[2]. The main limitation of NFS is its susceptibility to BMI and age, which may lead to a high false-positive rate[38].
Enhanced liver fibrosis (ELF) test
The ELF test is a direct biomarker assay that quantifies three serum markers involved in extracellular matrix metabolism: hyaluronic acid (HA), procollagen III N-terminal peptide (PIIINP), and tissue inhibitor of metalloproteinases-1 (TIMP-1), thereby providing more direct pathophysiological information on fibrosis[39]. Studies show that the ELF test has good diagnostic performance for detecting significant fibrosis, advanced fibrosis, and cirrhosis, with AUROC values of 0.811, 0.812, and 0.810, respectively[40]. Despite its diagnostic accuracy advantages, the ELF test has limited availability and higher cost, and its specificity may decrease in low-prevalence populations. Therefore, guidelines suggest its use as an alternative to imaging for identifying advanced liver fibrosis or as a supplementary assessment for patients with indeterminate screening results.
PRO-C3 and ADAPT score
PRO-C3 (procollagen III N-terminal peptide) is a direct serum biomarker that reflects active type III collagen formation during fibrogenesis, providing a real-time measure of fibroblast activity[41]. In a cohort of 431 biopsy-proven NAFLD patients, PRO-C3 levels progressively increased with fibrosis stage (rho = 0.50, P < 0.0001) and remained independently associated with advanced fibrosis after adjustment for multiple confounders (OR = 1.05, P = 0.003)[42].
Based on PRO-C3, the ADAPT score was developed to identify patients with advanced fibrosis (F ≥ 3). The score integrates four variables: Age, presence of DiAbetes, PRO-C3, and plaTelet count. In the derivation cohort (n = 150), ADAPT achieved an AUROC of 0.86 [95% confidence interval (CI): 0.79-0.91], which was superior to the AST to platelet ratio index (APRI) (0.73) and numerically higher than FIB-4 (0.78) and NFS (0.78). These findings were confirmed in an independent validation cohort (n = 281), with an AUROC of 0.87 (95%CI: 0.83-0.91), outperforming APRI (0.78, P = 0.0005) and NFS (0.79, P = 0.02), and comparable to FIB-4 (0.85, P = 0.32)[42]. Notably, ADAPT maintained robust performance across various subpopulations, including diabetics vs. non-diabetics and different BMI categories.These data support PRO-C3 and ADAPT as promising tools for identifying patients with advanced fibrosis and for monitoring treatment response in MASH. ADAPT was derived and validated in biopsy-proven NAFLD cohorts from Australia, the UK, and Japan.
LiverRisk score
The LiverRisk score is a next-generation serum scoring system. Derived from an international prospective cohort, it integrates eight variables: age, sex, and six standard laboratory parameters - AST, ALT, gamma-glutamyl transferase (GGT), fasting glucose, total cholesterol, and platelet count - to quantify liver-related mortality risk. Using three cut-offs (6, 10, and 15 points), the score classifies individuals into four risk levels (very low, low, medium, and high), providing a dynamic basis for clinical decision-making. In terms of diagnostic performance, the LiverRisk score achieves an AUROC of 0.83 for predicting liver stiffness ≥
Steatosis-Associated Fibrosis Estimator (SAFE) score
The SAFE score is a non-invasive assessment tool specifically designed for MASLD to optimize risk stratification in primary care settings[44]. It integrates readily available clinical parameters, including age, BMI, diabetes status, platelet count, AST, ALT, and globulin levels. Compared with traditional blood biomarkers, the SAFE score demonstrates superior ability to identify low-risk patients, effectively distinguishing mild fibrosis (F0-F1) from significant fibrosis (≥ F2), thereby reducing reliance on invasive tests. In NAFLD populations, the SAFE score outperforms the FIB-4 index and NFS, particularly in patients with metabolic risk factors such as obesity or T2D; however, its broader applicability requires further validation across diverse populations. The SAFE score was developed using the NASH Clinical Research Network observational cohort as the training set, and validated in the FLINT trial cohort and in a Stanford cohort with MRE-based fibrosis assessment. The LiverRisk score was derived and validated in large European general population cohorts[45-47].
LiverPRO score
The LiverPRO score is an innovative software tool designed for primary care settings, aiming to achieve efficient risk stratification using routine clinical data. The tool is highly flexible, automatically selecting 3-9 variables from a candidate pool of nine routine laboratory tests plus age, and generating 466 multivariable models to accommodate varying data availability across clinical settings. For diagnostic performance, the LiverPRO score achieves an AUROC of 0.86 for detecting LSM ≥ 8 kPa in the derivation cohort and 0.80 in the DECIDE validation cohort[48]. Validation data indicate that its diagnostic performance is comparable to that of the ELF and LiverRisk scores and significantly superior to traditional FIB-4 and MAFLD scores.
Agile scores
The Agile scoring system is an innovative assessment tool specifically developed for the MASLD population to address the clinical need for accurate diagnosis of advanced fibrosis and cirrhosis. The system includes two sub-scores: Agile 3+ for assessing advanced fibrosis (F3) and Agile 4 for cirrhosis (F4)[49]. A meta-analysis of seven studies (6,037 participants) showed that in MASLD patients, Agile 4 had a pooled sensitivity of 0.90 (95%CI: 0.80-0.95) for excluding cirrhosis (< 0.251) and a pooled specificity of 0.93 (95%CI: 0.86-0.97) for ruling in cirrhosis (≥ 0.565)[50]. Another external validation study showed that Agile 3+ had an AUROC of 0.86 for identifying F3 fibrosis and Agile 4 had an AUROC of 0.89 for identifying F4 fibrosis, though these values were not significantly different from the diagnostic accuracy of LSM alone. Agile scores have been validated in MASLD and ALD populations, but their performance in viral hepatitis is inferior to LSM[49].
Magnetic resonance imaging-aspartate aminotransferase (MAST) score and MRE combined with FIB-4 (MEFIB) index
The MAST score integrates MRI-PDFF, MRE-derived liver stiffness, and AST to identify patients with fibrotic NASH [NAFLD activity score (NAS) ≥ 4, F ≥ 2)]. In a validation cohort, it achieved an AUROC of 0.93 (95%CI: 0.88-0.97), with rule-out (< 0.165) and rule-in (> 0.242) cut-offs, outperforming FIB-4, NFS, and the FibroScan-AST (FAST) score. MAST was validated in tertiary care cohorts with a low prevalence of Fibro-NASH, reflecting real-world clinical settings[51].
The MEFIB index combines MRE ≥ 3.3 kPa and FIB-4 ≥ 1.6 as a binary rule-in for significant fibrosis (≥ F2). It demonstrated a PPV of 97.1% in the training cohort and 91.0% in an independent Japanese validation cohort[52].
Both scores are limited to specialized centers with MRE availability but offer high diagnostic accuracy for identifying candidates for pharmacotherapy and clinical trial enrichment.
FibroSure (FibroTest)
FibroSure (also known as FibroTest) is a proprietary algorithm-based assay that integrates several serum markers - alpha-2-macroglobulin (α2-M), haptoglobin (Hp), apolipoprotein A1 (ApoA1), GGT, and total bilirubin (TBil) - to assess the degree of liver fibrosis and necroinflammatory activity. In patients with NAFLD, the FibroTest (FibroSure) has demonstrated good diagnostic accuracy for advanced fibrosis and cirrhosis, with AUROCs of 0.86 for F2-F4 and 0.92 for F3-F4 in a prospective validation study[53]. However, it may be affected by acute inflammation or hemolysis. Therefore, guidelines recommend its combined use with other diagnostic modalities, such as VCTE, to provide a comprehensive assessment of liver pathology.
SECOND-LEVEL ASSESSMENT: IMAGING ELASTOGRAPHY TECHNIQUES
Imaging elastography techniques quantitatively measure the mechanical properties (stiffness) or physical attributes (attenuation) of liver tissue using physical principles such as shear waves or magnetic resonance, providing objective, organ-specific data. These techniques generate shear waves within the liver via external excitation and measure their propagation velocity to calculate liver stiffness values. During liver fibrogenesis, extracellular matrix deposition and cross-linking increase hepatic stiffness; thus, liver stiffness values directly reflect the extent of fibrotic accumulation [Table 3].
Comparison of diagnostic performance of major imaging techniques
| Technique | Principle | Diagnostic performance (Advanced fibrosis) | Advantages | Limitations | Clinical positioning |
| VCTE[54] | Shear wave velocity → LSM | AUROC 0.82-0.88 | Fast, reproducible, simultaneous CAP assessment | Obesity, ascites affect accuracy | Core second-level assessment tool |
| MRE[55] | Shear wave imaging → whole-liver stiffness map | AUROC 0.89-0.94 | Whole-liver assessment, highest accuracy | High cost, limited accessibility | Most accurate non-invasive imaging technique for fibrosis staging |
| SWE[57-59] | Ultrasound shear wave real-time measurement | Comparable to VCTE | Advantage in obese patients, real-time imaging | Lower sensitivity for early fibrosis | Alternative or supplement to VCTE |
| TAI/TSI[62,63] | Ultrasound attenuation/scatter analysis | Good diagnostic performance for steatosis and inflammation | Integrated workflow, high platform ubiquity | Lack of standardization, operator-dependent | Primary screening, inflammation assessment |
VCTE
VCTE is the most widely used non-invasive imaging assessment tool. Its core technology generates shear waves in the liver via transient vibration, measures their propagation speed to calculate liver stiffness, and simultaneously uses CAP to quantify hepatic steatosis. VCTE has good diagnostic accuracy for advanced fibrosis (F3-F4), with reported AUROC values ranging from 0.82 to 0.88 for detecting F3-F4 fibrosis[54]. However, the diagnostic accuracy of VCTE can be compromised by liver inflammation, cholestasis, and hepatic congestion - all of which can transiently elevate stiffness measurements independent of fibrosis stage, contributing to spectrum bias - as well as narrow intercostal spaces. In addition, the failure rate is significantly higher in patients with severe obesity, primarily due to increased skin-to-capsule distance and thicker subcutaneous adipose tissue, which attenuate shear wave propagation. Therefore, in clinical practice, VCTE is often recommended as a second-line assessment tool after serum scoring (e.g., FIB-4) for risk stratification and dynamic monitoring of disease progression[2].
MRE
MRE is currently the most accurate non-invasive imaging technique for assessing liver fibrosis. It combines conventional magnetic resonance imaging (MRI) with elastography principles to generate visual maps that reflect liver stiffness distribution across the entire organ[55]. MRE demonstrates high diagnostic accuracy for significant fibrosis (≥ F2), with an AUROC of 0.89, and is widely regarded as the most accurate non-invasive method for fibrosis staging, although liver biopsy remains the definitive histological reference standard[14]. This technique is particularly advantageous in obese patients and for detecting early-stage fibrosis (F0-F2), because its diagnostic performance is less affected by abdominal wall thickness[56]. Nevertheless, widespread use of MRE is limited by high cost, limited equipment availability, and high patient cooperation requirements. It is currently used mainly as a second- or third-line tool in specialized centers for patients with inconclusive serum or VCTE results, those requiring precise diagnosis, or those enrolled in clinical trials.
Shear wave elastography (SWE)
SWE is an ultrasound-based real-time technique for measuring liver stiffness, with diagnostic accuracy comparable to that of VCTE[57]. However, its sensitivity for early-stage fibrosis remains relatively low[58].
The core advantage of SWE lies in its ability to provide objective, quantitative, and organ-specific liver stiffness data, with diagnostic accuracy significantly higher than that of serum scores, especially for detecting at least moderate fibrosis[57-59]. Some studies have suggested that SWE may be feasible in patients with obesity when using deep-penetration probes, although measurement reliability is still largely dependent on skin-to-capsule distance and adequate acoustic windows. Limitations include higher cost than serum tests, and measurement accuracy can be affected by operator skill, severe obesity (particularly with increased skin-to-capsule distance), ascites, and acute hepatitis[57,60]. Furthermore, as with MRE, advanced imaging techniques such as SWE remain poorly accessible in primary care.
Quantitative ultrasound techniques
Conventional B-mode ultrasonography is the most widely available and affordable imaging modality for hepatic steatosis. It relies on qualitative features such as increased liver echogenicity (bright liver), hepatorenal echo contrast, blurring of intrahepatic vessel margins, and posterior beam attenuation. Its advantages include low cost, broad availability in primary care, lack of radiation, and feasibility for repeated assessments. However, its sensitivity for detecting mild steatosis is limited; it generally requires hepatic fat content > 20%-30% to be reliably detected, and its accuracy is reduced in obesity and by operator dependence[61].
To improve standardization, semiquantitative ultrasonographic indices have been developed, including the hepatorenal index (HRI), the ultrasound fatty liver index (US-FLI), and graded scoring systems (mild, moderate, severe). These indices provide a more reproducible estimate of steatosis severity than qualitative B-mode alone and can detect mild steatosis in some patients, although they remain operator-dependent and are less accurate than MRI-PDFF or CAP for quantifying small changes in hepatic fat. Nevertheless, given their affordability and broad availability, conventional and semiquantitative ultrasonography remain useful first-line tools for identifying hepatic steatosis in primary care and for large-scale screening, particularly in resource-limited settings.
Quantitative ultrasound techniques, such as tissue attenuation imaging (TAI) and tissue scatter distribution imaging (TSI), represent major advances in assessing hepatic steatosis on ultrasound platforms. TAI quantifies hepatic fat content by measuring the rate of ultrasound energy attenuation in liver tissue, and its attenuation coefficient correlates highly with histological steatosis grade. TSI evaluates tissue microstructure by analyzing the statistical distribution of ultrasound backscatter signals. Notably, studies have reported that TSI parameters correlate with histological activity scores; however, it is important to emphasize that, like all current NITs, TSI cannot directly assess microscopic features such as lobular inflammation or hepatocyte ballooning, which require histological examination[2]. These two techniques extract information from different physical dimensions (energy attenuation vs. structural scattering), enabling simultaneous quantitative assessment of the two core pathological changes in MASLD - steatosis and inflammatory activity.
In terms of diagnostic performance, TAI has good accuracy for assessing hepatic steatosis, whereas TSI shows strong performance in detecting inflammation. The combined model of TSI and SWE demonstrates excellent diagnostic performance for predicting MASH[62]. The principal value of this technique is that it equips widely available conventional ultrasound devices to perform accurate staging and risk stratification, serving as a bridge between primary screening and specialized assessment. Ideal applications include immediate quantitative assessment of incidentally identified hepatic steatosis in primary care, or use as a complement to VCTE in specialized clinics to evaluate inflammatory activity risk.
Compared with existing technologies, TAI can cross-validate with CAP for fat quantification, but its key advantage lies in performing TAI, TSI, and conventional ultrasound on the same device during a single examination[62,63]. Although its quantitative accuracy does not yet match that of MRI-PDFF, quantitative ultrasound offers substantial advantages in accessibility, cost, and convenience[63]. It provides direct tissue information with greater organ specificity than indirect serum models. Notable advantages include high platform ubiquity, an integrated “conventional ultrasound + TAI + TSI + SWE” workflow, and no additional cost or risk. Current challenges include the need for further research to standardize scanning protocols, establish diagnostic thresholds, and overcome operator dependence. Future trends involve deep integration with AI algorithms to develop more powerful automated diagnostic and predictive models.
Composite scoring systems represent one approach. The FAST score, which combines VCTE-derived liver stiffness with serum AST levels, identifies individuals at high risk for fibrotic MASH (i.e., MASH with significant fibrosis). A meta-analysis of 12 studies comprising 5,835 patients reported a pooled sensitivity of 89%, specificity of 89%, and NPV of 92% at optimal cut-offs, demonstrating excellent exclusion efficacy[64].
EMERGING APPROACHES: AI AND MULTI-MODAL INTEGRATION MODELS
Beyond established serum and imaging biomarkers, an emerging area of investigation is the application of AI and multi-modal integration models. These approaches remain largely investigational and are not yet incorporated into routine clinical guidelines, but they hold promise for more accurate risk prediction and early detection through analysis of high-dimensional data. It is important to note that this third level is a conceptual framework proposed by the authors to structure the discussion, rather than an established guideline-endorsed pathway.
It is important to distinguish between two categories of AI-related tools. First, several radiomics-based models - for example, deep learning algorithms applied to elastography images - have been developed and validated in large, multicenter cohorts, showing improved diagnostic accuracy over conventional methods. Second, most other AI applications, including large language models (LLM) and complex multi-modal integration systems, remain in early research stages without prospective validation; their clinical utility has not yet been established. The discussion below focuses primarily on this latter, emerging category.
An emerging trend is the application of machine learning and deep learning algorithms to integrate data from different dimensions and modalities, achieving predictive and diagnostic capabilities beyond those of traditional models. By detecting complex patterns in high-dimensional, non-linear data, these algorithms can identify potential biomarkers and risk features that traditional statistical methods might miss.
Multi-parameter prediction models integrating clinical, biomarker, and imaging data have been explored in multiple studies. A systematic review of 26 studies reported AUROC ranges of 0.76-0.95 for AI-based MASH diagnosis and 0.72-0.94 for detecting ≥ F2 fibrosis, suggesting potential advantages of multi-modal integration, although most studies were retrospective and lacked prospective validation[65].
Radiomics and AI-assisted analysis employ deep learning to extract subtle microstructural features from ultrasound, computed tomography (CT), or MRI for early identification and precise subtyping. An international multicenter study developed a deep learning radiomics model based on 9,472 two-dimensional SWE (2D-SWE) images, achieving a diagnostic AUROC of 0.89, which was significantly better than that of conventional SWE (0.83)[66].
AI models can process high-dimensional data, offering potential for earlier diagnosis, more accurate prognosis, and novel biomarker discovery. However, most current studies remain at the preclinical stage, lacking large-scale prospective validation; issues include insufficient model interpretability and a lack of cross-platform standardization. As a key driver of precision medicine for MASLD, AI and multi-modal integration models are primarily intended for complex case evaluation, early warning, and dynamic monitoring of treatment response, pointing toward the future of individualized and dynamic assessment.
CLINICAL LOGIC OF THE THREE-TIER ASSESSMENT SYSTEM
The three-tier framework outlined above is proposed by the authors as a conceptual model to facilitate understanding of the current NIT landscape, rather than a formal clinical pathway endorsed by practice guidelines. Established guideline-recommended pathways, such as those from EASL, follow a validated two-step strategy beginning with FIB-4, followed by elastography or ELF testing when indicated[2]. In this approach, patients with FIB-4 < 1.3 are considered low-risk and managed in primary care, while those with indeterminate (1.3-2.67) or high-risk (> 2.67) scores proceed to second-line testing with VCTE or ELF for further stratification[67] [Figure 1]. Beyond its role in routine clinical care, the combination of FIB-4 and LSM (FIB-4 + VCTE) has also been specifically evaluated for enriching clinical trial populations; this dual-marker strategy reduces unnecessary referrals and improves the pre-test probability of identifying patients with advanced fibrosis, making it a practical tool for screening candidates for MASH pharmacotherapy trials[2,67]. However, NIT-based eligibility criteria for MASH pharmacotherapy only partially align with histological F2-F3 fibrosis[68], suggesting that NITs cannot yet fully replace histological assessment. Recent discussions have also highlighted the need to propel MASLD trials into the era of NITs[69], supporting the use of FIB-4 plus LSM for trial enrichment while acknowledging the need for further validation. Notably, in certain high-risk populations such as patients with T2D, some guidelines suggest that VCTE may be considered as a first-line test rather than following the FIB-4-first algorithm, given the higher prevalence of advanced fibrosis and the suboptimal specificity of FIB-4 in this population[2].
Figure 1. Proposed clinical algorithm for NIT-based risk stratification of MASLD in primary care and hepatology settings. This algorithm is proposed by the authors based on current guideline recommendations[2,33]. FIB-4 thresholds are adjusted for patients aged ≥ 65 years. ELF: Enhanced liver fibrosis; FIB-4: fibrosis-4 index; kPa: kilopascal; LSM: liver stiffness measurement; MASLD: metabolic dysfunction-associated steatotic liver disease; MRE: magnetic resonance elastography; NIT: non-invasive test; VCTE: vibration-controlled transient elastography.
In this framework, serum scores (first tier) enable low-cost initial risk stratification across broad populations; imaging elastography (second tier) provides accurate fibrosis staging for patients with indeterminate or high-risk results; and emerging AI-based approaches (third tier) remain investigational but hold promise for precise subtyping and individualized risk prediction in the future.
Novelty relative to existing frameworks. Existing guideline pathways (e.g., EASL) and recent reviews describe two-step or multitier systems that are organized primarily by test modality or technical complexity - blood-based scores followed by imaging, and in some proposals, followed by metabolomic or MRI-based integration[70,71]. The present three-tier framework differs in its organizing principle. It is structured not by the sophistication of the test, but by the clinical question that each tier is designed to answer: whether a patient can be safely managed in primary care (Tier 1), how to achieve precise fibrosis staging with available imaging in specialty settings (Tier 2), and which emerging technologies - though not yet guideline-endorsed - are poised to shift the field from “staging” toward “subtyping” and longitudinal monitoring (Tier 3)[72]. This distinction matters because a modality-driven algorithm implicitly prioritizes diagnostic accuracy as the sole metric of value, whereas a clinically driven framework explicitly incorporates setting-specific prevalence, actionability, and the evolving role of NITs in treatment selection and monitoring - dimensions that existing reviews have not systematically integrated into a single conceptual structure[73].
CONCLUSION AND FUTURE PERSPECTIVES
MASLD has become the leading cause of chronic liver disease worldwide. Its close association with metabolic diseases such as obesity and T2D makes early identification and precise stratification core clinical challenges[2]. This review systematically summarizes the current status and advances in non-invasive assessment techniques for MASLD. Serum scoring systems, exemplified by the FIB-4 index, are indispensable for primary screening and ruling out low-risk individuals because of their low cost and easy accessibility. Imaging elastography techniques, represented by VCTE and MRE, provide objective and accurate fibrosis staging through quantitative measurement of liver stiffness and fat content. AI and multi-modal integration models represent the future direction, promising a shift from “staging” to “subtyping”.
Each of the three assessment methods has distinct advantages and limitations in clinical practice. The choice of approach should be individualized based on the clinical scenario, available resources, and patient characteristics.
Despite significant advances in non-invasive assessment techniques, multiple challenges remain in clinical practice. Regarding primary care accessibility, imaging devices such as VCTE are underutilized in primary care settings, with real-world data showing that only 33.5% of patients at high risk of fibrosis are referred to specialists, representing an overall management gap of 28.0%[74]. Regarding technical standardization, measurement consistency across different devices and operators needs improvement, and quantitative ultrasound and AI models lack unified scanning protocols and diagnostic thresholds; the G-MASLD international multicenter study found that the AUROC of FIB-4 for diagnosing advanced fibrosis was as low as 0.75 in Latin America but reached 0.84 in the Middle East and North Africa, indicating significant regional heterogeneity[75]. High-precision techniques such as MRE and AI models are costly. Although sequential screening strategies (FIB-4 combined with VCTE or ELF) can reduce unnecessary referrals by more than 40% with lower overall costs, further health economics research is needed to optimize resource allocation[67]. Finally, regarding genetic and phenotypic heterogeneity, existing NITs mainly focus on fibrosis staging and have not yet fully integrated genetic risk factors such as PNPLA3 and TM6SF2; integration could bring AUROC improvements of 0.053 and 0.058 for NFS and FIB-4, respectively, but the absolute gains are limited[76].
Future directions include multi-omics integration and precise subtyping, moving from “staging” to “subtyping” by combining genomics, proteomics [PRO-C3, cytokeratin-18 (CK-18)], metabolomics, and imaging features to build multi-modal risk prediction models. Regarding dynamic monitoring and digital health, the approval of resmetirom and semaglutide[20], along with repeatable, low-cost portable ultrasound and wearable sensors, will shift MASLD management from “one-time diagnosis” to “continuous dynamic management”. The availability of two distinct pharmacotherapy classes further underscores the need for robust NIT-based monitoring strategies[77]. In terms of regulatory recognition, the FDA accepted a Letter of Intent for the qualification of VCTE-based LSM as a reasonably likely surrogate endpoint for non-cirrhotic MASH clinical trials in 2025[17] , marking a shift from the histology era to the non-invasive era in drug development. For AI-empowered clinical decision-making, preliminary studies have explored the use of AI-assisted systems that integrate electronic health records to automatically calculate FIB-4 and flag potential management gaps[74]. Similarly, early reports on LLM tools such as Fibro-GPT have suggested potential utility in detecting advanced fibrosis and predicting hepatic decompensation, but these findings require prospective validation before clinical application can be recommended[78]. Finally, regarding global collaboration and resource optimization, cross-regional collaborative networks should be established to unify NIT operating standards and data specifications, and to develop tiered screening strategies that ensure equitable access.
In summary, NIT techniques for MASLD have evolved from supportive tools to central components of comprehensive disease management. Although challenges remain in standardization, accessibility, and cost-effectiveness, multi-omics integration, AI advancement, and regulatory recognition will continue to drive NITs toward greater precision, adaptability, and sophistication. Ultimately, they will enable full-cycle precision management from screening to treatment, improving patient outcomes and reducing the global disease burden.
DECLARATIONS
Authors’ contributions
Performed the literature search: Su N, Zhou D
Led the drafting of the manuscript: Su N, Zhou D
Critically revised the manuscript for important intellectual content: Zhou D, Fan J
Availability of data and materials
Not applicable.
AI and AI-assisted tools statement
Not applicable.
Financial support and sponsorship
None.
Conflicts of interest
Fan J is an Editorial Board Member of Metabolism and Target Organ Damage. Fan J was not involved in any steps of editorial processing, notably including reviewers’ selection, manuscript handling and decision making. The other authors declare that there are no conflicts of interest.
Ethical approval and consent to participate
Not applicable.
Consent for publication
Not applicable.
Copyright
© The Author(s) 2026.
REFERENCES
1. Israelsen M, Francque S, Tsochatzis EA, Krag A. Steatotic liver disease. Lancet. 2024;404:1761-78.
2. European Association for the Study of the Liver (EASL), European Association for the Study of Diabetes (EASD), European Association for the Study of Obesity (EASO). EASL-EASD-EASO Clinical Practice Guidelines on the management of metabolic dysfunction-associated steatotic liver disease (MASLD). J Hepatol. 2024;81:492-542.
3. Huang DQ, Wong VWS, Rinella ME, et al. Metabolic dysfunction-associated steatotic liver disease in adults. Nat Rev Dis Primers. 2025;11:14.
4. Zheng H, Sechi LA, Navarese EP, Casu G, Vidili G. Metabolic dysfunction-associated steatotic liver disease and cardiovascular risk: a comprehensive review. Cardiovasc Diabetol. 2024;23:346.
5. Mantovani A, Csermely A, Petracca G, et al. Non-alcoholic fatty liver disease and risk of fatal and non-fatal cardiovascular events: an updated systematic review and meta-analysis. Lancet Gastroenterol Hepatol. 2021;6:903-13.
6. Younossi ZM, Razavi H, Sherman M, et al. Addressing the high and rising global burden of metabolic dysfunction-associated steatotic liver disease (MASLD) and metabolic dysfunction-associated steatohepatitis (MASH): from the growing prevalence to payors’ perspective. Aliment Pharmacol Ther. 2025;61:1467-78.
7. Kaylan KB, Paul S. NAFLD no more: a review of current guidelines in the diagnosis and evaluation of metabolic dysfunction-associated steatotic liver disease (MASLD). Curr Diab Rep. 2024;25:5.
8. Chowdhury AB, Mehta KJ. Liver biopsy for assessment of chronic liver diseases: a synopsis. Clin Exp Med. 2023;23:273-85.
9. Tincopa MA, Loomba R. Non-invasive diagnosis and monitoring of non-alcoholic fatty liver disease and non-alcoholic steatohepatitis. Lancet Gastroenterol Hepatol. 2023;8:660-70.
10. Sanyal AJ, Castera L, Wong VW. Noninvasive assessment of liver fibrosis in NAFLD. Clin Gastroenterol Hepatol. 2023;21:2026-39.
11. Zoncapè M, Liguori A, Tsochatzis EA. Non-invasive testing and risk-stratification in patients with MASLD. Eur J Intern Med. 2024;122:11-9.
12. Abdelhameed F, Kite C, Lagojda L, et al. Non-invasive scores and serum biomarkers for fatty liver in the era of metabolic dysfunction-associated steatotic liver disease (MASLD): a comprehensive review from NAFLD to MAFLD and MASLD. Curr Obes Rep. 2024;13:510-31.
13. Yu JH, Lee HA, Kim SU. Noninvasive imaging biomarkers for liver fibrosis in nonalcoholic fatty liver disease: current and future. Clin Mol Hepatol. 2023;29:S136-49.
14. Chon YE, Jin YJ, An J, et al. Optimal cut-offs of vibration-controlled transient elastography and magnetic resonance elastography in diagnosing advanced liver fibrosis in patients with nonalcoholic fatty liver disease: a systematic review and meta-analysis. Clin Mol Hepatol. 2024;30:S117-33.
15. Zhang H, Wu X, Ni W, et al. Application of machine learning and deep learning in metabolic dysfunction-associated steatotic liver disease: a systematic review and meta-analysis. J Adv Res. 2026;83:933-46.
16. Yin C, Zhang H, Du J, Zhu Y, Zhu H, Yue H. Artificial intelligence in imaging for liver disease diagnosis. Front Med. 2025;12:1591523.
17. FDA. FDA accepts proposal for reasonably likely surrogate endpoint for ‘MASH’ all-cause mortality or liver-related events. Available from: https://www.fda.gov/drugs/drug-alerts-and-statements/fda-accepts-proposal-reasonably-likely-surrogate-endpoint-mash-all-cause-mortality-or-liver-related. [Last accessed on 28 Oct 2026].
18. Petta S, Targher G, Romeo S, et al. The first MASH drug therapy on the horizon: current perspectives of resmetirom. Liver Int. 2024;44:1526-36.
19. Harrison SA, Bedossa P, Guy CD, et al. ; MAESTRO-NASH Investigators. A phase 3, randomized, controlled trial of resmetirom in NASH with liver fibrosis. N Engl J Med. 2024;390:497-509.
20. Sanyal AJ, Newsome PN, Kliers I, et al. ; ESSENCE Study Group. Phase 3 trial of semaglutide in metabolic dysfunction-associated steatohepatitis. N Engl J Med. 2025;392:2089-99.
21. Rinella ME, Lazarus JV, Ratziu V, et al. ; NAFLD Nomenclature consensus group. A multisociety Delphi consensus statement on new fatty liver disease nomenclature. Hepatology. 2023;78:1966-86.
22. Eslam M, Sanyal AJ, George J; International Consensus Panel. MAFLD: a consensus-driven proposed nomenclature for metabolic associated fatty liver disease. Gastroenterology. 2020;158:1999-2014.e1.
23. Younossi ZM, Alqahtani SA, Alswat K, et al. ; Global NASH Council. Global survey of stigma among physicians and patients with nonalcoholic fatty liver disease. J Hepatol. 2024;80:419-30.
24. Younossi ZM, AlQahtani SA, Funuyet-Salas J, et al. ; Global NASH Council. The impact of stigma on quality of life and liver disease burden among patients with nonalcoholic fatty liver disease. JHEP Rep. 2024;6:101066.
25. Ludwig J, Viggiano TR, Mcgill DB, Ott BJ. Nonalcoholic steatohepatitis: mayo clinic experiences with a hitherto unnamed disease. Mayo Clinic Proceedings. 1980;55:434-8.
26. Younossi ZM, de Avila L, Petta S, et al. ; Global NASH/MASH Council (GNC). Diagnostic accuracy of noninvasive tests for metabolic dysfunction-associated steatotic liver disease across age, type 2 diabetes, and obesity subgroups: a multinational study. Clin Gastroenterol Hepatol. 2026;24:2453-64.
27. Forlano R, Stanic T, Jayawardana S, et al. Derivation and validation of the BIMAST score for predicting the presence of fibrosis due to metabolic dysfunction-associated steatotic liver disease among diabetic patients in the community. PLoS One. 2024;19:e0307500.
28. Choudhary NS, Kuchay MS, Dhampalwar S, et al. Performance of fibrosis-4 and NAFLD fibrosis score for screening liver fibrosis in Indian individuals with type 2 diabetes: a prospective cross-sectional study. Diabetes Metab Syndr. 2026;20:103380.
29. Sterling RK, Lissen E, Clumeck N, et al. ; APRICOT Clinical Investigators. Development of a simple noninvasive index to predict significant fibrosis in patients with HIV/HCV coinfection. Hepatology. 2006;43:1317-25.
30. Vali Y, Lee J, Boursier J, et al. ; Liver Investigation: Testing Marker Utility in Steatohepatitis (LITMUS) consortium investigators. Biomarkers for staging fibrosis and non-alcoholic steatohepatitis in non-alcoholic fatty liver disease (the LITMUS project): a comparative diagnostic accuracy study. Lancet Gastroenterol Hepatol. 2023;8:714-25.
31. Oh JH, Ahn SB, Cho S, Nah EH, Yoon EL, Jun DW. Diagnostic performance of non-invasive tests in patients with MetALD in a health check-up cohort. J Hepatol. 2024;81:772-80.
32. Layard B, Magill J, Reid C, McAllister P, Toland N, Gilmore S. P18 the great fatty liver showdown: comparison of FIB-4 score to liver stiffness measurement (LSM) on fibroscan in metabolic-dysfunction associated steatosis liver disease (MASLD). Gut. 2025;74:A26-A.
33. European Association for the Study of the Liver. EASL Clinical Practice Guidelines on non-invasive tests for evaluation of liver disease severity and prognosis - 2021 update. J Hepatol. 2021;75:659-89.
34. van Kleef LA, Strandberg R, Pustjens J, et al. FIB-4-based referral pathways have suboptimal accuracy to identify increased liver stiffness and incident advanced liver disease. Clin Gastroenterol Hepatol. 2026;24:733-42.
35. Heyens LJM, van Malde DPA, Dogay Us G, et al. ; MASLD research group. Is FIB-4 the right tool for screening for liver fibrosis? Ann Hepatol 2025;31:102176.
36. Serra A, Palmieri E, Burzo ML, et al. FIB-4 index as a non-invasive biomarker of congestion and prognosis in heart failure. J Clin Med. 2026;15:4448.
37. Angulo P, Hui JM, Marchesini G, et al. The NAFLD fibrosis score: a noninvasive system that identifies liver fibrosis in patients with NAFLD. Hepatology. 2007;45:846-54.
38. Li G, Zhang X, Lin H, Liang LY, Wong GL, Wong VW. Non-invasive tests of non-alcoholic fatty liver disease. Chin Med J. 2022;135:532-46.
39. Rosenberg WM, Voelker M, Thiel R, et al. ; European Liver Fibrosis Group. Serum markers detect the presence of liver fibrosis: a cohort study. Gastroenterology. 2004;127:1704-13.
40. Hinkson A, Lally H, Gibson H, et al. Meta-analysis: enhanced liver fibrosis test to identify hepatic fibrosis in chronic liver diseases. Aliment Pharmacol Ther. 2023;57:750-62.
41. Nielsen MJ, Nedergaard AF, Sun S, et al. The neo-epitope specific PRO-C3 ELISA measures true formation of type III collagen associated with liver and muscle parameters. Am J Transl Res. 2013;5:303-15.
42. Daniels SJ, Leeming DJ, Eslam M, et al. ADAPT: an algorithm incorporating PRO-C3 accurately identifies patients with NAFLD and advanced fibrosis. Hepatology. 2019;69:1075-86.
43. Serra-Burriel M, Juanola A, Serra-Burriel F, et al. ; LiverScreen Consortium Investigators. Development, validation, and prognostic evaluation of a risk score for long-term liver-related outcomes in the general population: a multicohort study. Lancet. 2023;402:988-96.
44. Sripongpun P, Kim WR, Mannalithara A, et al. The steatosis-associated fibrosis estimator (SAFE) score: a tool to detect low-risk NAFLD in primary care. Hepatology. 2023;77:256-67.
45. Li M, Lin Y, Yu H, et al. The steatosis-associated fibrosis estimator (SAFE) outperformed the FIB-4 score in screening the population for liver disease. Ann Hepatol. 2024;29:101516.
46. Kaewdech A, Sripongpun P, Treeprasertsuk S, Charatcharoenwitthaya P, Chan WK, Kim WR; GO ASIA Study Group. Sequential SAFE score and transient elastography for detecting significant fibrosis in asian patients with MASLD. Clin Gastroenterol Hepatol. 2024;22:2535-7.
47. Kim K, Lee HW, Lee JS, Kim MN, Park JY. Steatosis-associated fibrosis estimator score in Asian patients with metabolic dysfunction-associated steatotic liver disease. Yonsei Med J. 2026;67:104-11.
48. Lindvig KP, Thorhauge KH, Hansen JK, et al. Development, validation, and prognostic evaluation of LiverPRO for the prediction of significant liver fibrosis in primary care: a prospective cohort study. Lancet Gastroenterol Hepatol. 2025;10:55-67.
49. Papatheodoridi M, De Ledinghen V, Lupsor-Platon M, et al. Agile scores in MASLD and ALD: external validation and their utility in clinical algorithms. J Hepatol. 2024;81:590-9.
50. Malandris K, Katsoula A, Liakos A, et al. Diagnostic accuracy of Agile-4 score for liver cirrhosis in patients with metabolic dysfunction-associated steatotic liver disease. A systematic review and meta-analysis of diagnostic test accuracy studies. Diabetes Obes Metab. 2025;27:1406-14.
51. Noureddin M, Truong E, Gornbein JA, et al. MRI-based (MAST) score accurately identifies patients with NASH and significant fibrosis. J Hepatol. 2022;76:781-7.
52. Jung J, Loomba RR, Imajo K, et al. MRE combined with FIB-4 (MEFIB) index in detection of candidates for pharmacological treatment of NASH-related fibrosis. Gut. 2021;70:1946-53.
53. Ratziu V, Massard J, Charlotte F, et al. ; LIDO Study Group, CYTOL study group. Diagnostic value of biochemical markers (FibroTest-FibroSURE) for the prediction of liver fibrosis in patients with non-alcoholic fatty liver disease. BMC Gastroenterol. 2006;6:6.
54. Mózes FE, Lee JA, Selvaraj EA, et al. ; LITMUS Investigators. Diagnostic accuracy of non-invasive tests for advanced fibrosis in patients with NAFLD: an individual patient data meta-analysis. Gut. 2022;71:1006-19.
55. Liang JX, Ampuero J, Niu H, et al. ; LITMUS Consortium Investigators. An individual patient data meta-analysis to determine cut-offs for and confounders of NAFLD-fibrosis staging with magnetic resonance elastography. J Hepatol. 2023;79:592-604.
56. Singh S, Venkatesh SK, Loomba R, et al. Magnetic resonance elastography for staging liver fibrosis in non-alcoholic fatty liver disease: a diagnostic accuracy systematic review and individual participant data pooled analysis. Eur Radiol. 2016;26:1431-40.
57. Bauer DJM, Nixdorf L, Dominik N, et al. The deep abdominal ultrasound transducer (DAX) increases the success rate and diagnostic accuracy of shear wave elastography for liver fibrosis assessment in patients with obesity-A prospective biopsy-controlled study. Aliment Pharmacol Ther. 2024;60:70-82.
58. Indre MG, Leucuta DC, Lupsor-Platon M, et al. Diagnostic accuracy of 2D-SWE ultrasound for liver fibrosis assessment in MASLD: a multilevel random effects model meta-analysis. Hepatology. 2025;82:454-69.
59. Sun M, Zhong M, Luo F, Lan M, Zhang X, Ma Z. Assessment of liver fibrosis with multisample point shear wave elastography in obese patients with metabolic dysfunction-associated steatotic liver disease. Acad Radiol. 2025;32:5150-61.
60. Osakabe K, Sugimoto K, Takai H, et al. Reliability of liver stiffness measurements using shear wave elastography: impact of skin-to-capsule distance and subcutaneous tissue structure. J Med Ultrason. 2026;53:147-56.
61. Hernaez R, Lazo M, Bonekamp S, et al. Diagnostic accuracy and reliability of ultrasonography for the detection of fatty liver: a meta-analysis. Hepatology. 2011;54:1082-90.
62. Huang TY, Li ZY, Tian J, et al. Metabolic dysfunction-associated steatotic liver disease at quantitative US: international prospective study. Radiology. 2025;316:e242564.
63. Li X, Sun Z, Liu W, et al. Methodology exploration and reproducibility evaluation of TAI and TSI for quantitative ultrasound assessment of hepatic steatosis. Heliyon. 2024;10:e31904.
64. Ravaioli F, Dajti E, Mantovani A, Newsome PN, Targher G, Colecchia A. Diagnostic accuracy of FibroScan-AST (FAST) score for the non-invasive identification of patients with fibrotic non-alcoholic steatohepatitis: a systematic review and meta-analysis. Gut. 2023;72:1399-409.
65. Njei B, Al-Ajlouni YA, Lemos SY, et al. AI-based models for risk prediction in MASLD: a systematic review. Dig Dis Sci. 2026;71:1987-2014.
66. Lu X, Zhang H, Kuroda H, et al. Deep learning radiomics of elastography for diagnosing compensated advanced chronic liver disease: an international multicenter study. Vis Comput Ind Biomed Art. 2025;8:19.
67. Younossi ZM, Paik JM, Henry L, Pollock RF, Stepanova M, Nader F. Economic evaluation of non-invasive test pathways for high-risk metabolic dysfunction-associated steatotic liver disease (MASLD) in the United Kingdom (UK). Ann Hepatol. 2025;30:101789.
68. Moreau C, Roux M, Riou J, et al. Personalized prediction of the individual risk of liver-related events in metabolic dysfunction-associated steatotic liver disease using the dynamics of noninvasive tests. Clin Gastroenterol Hepatol. 2026;Epub ahead of print.
69. Lian LY, Liu WY, Li W, et al. Propelling MASLD trials into the era of non-invasive tests. Lancet Gastroenterol Hepatol. 2026;11:869-71.
70. Mironova M, Loomba R. Clinical use of noninvasive testing for liver fibrosis in metabolic dysfunction-associated steatotic liver disease. Clin Gastroenterol Hepatol. 2026;24:2370-3.
71. Kalafateli M, Aydin BS, Polat B, et al. Metabolic-associated steatotic liver disease (MASLD): how I evolved my approach to diagnosis and staging. Frontline Gastroenterol. 2026;17:250-61.
72. Alghzawi HM, Sahu S, Rana A, Mwita R, Gundapaneni S, Dahiya D. Integrated serum metabolomics and MRI biomarkers for MASLD: a practical framework for noninvasive staging and monitoring. Abdom Radiol. 2026;Epub ahead of print.
73. van Eekhout KMA, Broekman LD, de Jong VD, et al. ; GRIPonMASH consortium. Care pathways for metabolic dysfunction-associated steatotic liver disease (MASLD): a state-of-the-art review. Liver Int. 2026;46:e70603.
74. Ebiai R, McNair J, Shuaibi S, et al. Unrecognized fibrosis risk in MASLD: a real-world analysis and the case for AI-augmented stratification. Gastro Hep Adv. 2026;5:100857.
75. Younossi ZM, de Avila L, Petta S, et al. ; Global NASH/MASH Council (GNC). Global performance of non-invasive tests in MASLD: Insights from the G-MASLD study. Hepatology. 2026;84:161-74.
76. Kim DY, Zhang HS, Lee JS, et al. Integration of PNPLA3 and TM6SF2 genotypes provides incremental improvement in advanced fibrosis prediction among MASLD patients with type 2 diabetes mellitus. JHEP Rep. 2026;8:101713.
77. Feng G, Wong VW, Targher G, Byrne CD, Zheng MH. Non-invasive tests of fibrosis in the management of MASLD: revolutionising diagnosis, progression and regression monitoring. Gut. 2025;74:1741-50.
Cite This Article
 Open Access
How to Cite
Su N, Zhou D, Fan J. Advances in the non-invasive assessment of metabolic dysfunction-associated steatotic liver disease. Metab Target Organ Damage. 2026;6:66. https://dx.doi.org/10.20517/mtod.2026.119
Download Citation
Export Citation File:
Type of Import
Tips on Downloading Citation
Citation Manager File Format
Type of Import
Direct Import: When the Direct Import option is selected (the default state), a dialogue box will give you the option to Save or Open the downloaded citation data. Choosing Open will either launch your citation manager or give you a choice of applications with which to use the metadata. The Save option saves the file locally for later use.
Indirect Import: When the Indirect Import option is selected, the metadata is displayed and may be copied and pasted as needed.
About This Article
Special Topic
Copyright

Data & Comments
Data
0







Comments
Comments must be written in English. Spam, offensive content, impersonation, and private information will not be permitted. If any comment is reported and identified as inappropriate content by OAE staff, the comment will be removed without notice. If you have any queries or need any help, please contact us at support@oaepublish.com.